Try the questions in the test above first, then open each one here to see the correct answer and why every other option is wrong.
01A patient with a recent heart attack suddenly deteriorates after the papillary muscle supporting the mitral valve stops working. What is the direct mechanical result?
Practice question Unit: Cardiac Anatomy
AMitral cusps prolapse and blood leaks backward ✓ Correct answer
Without papillary muscle tension on the chordae, the mitral cusps prolapse into the left atrium and blood flows backward, causing rapid deterioration.
BPulmonary veins drain into the right atrium instead
Pulmonary veins always enter the left atrium; papillary muscle failure cannot redirect them to the right side of the heart.
CAortic valve cusps cannot open during ventricular contraction
Aortic valve cusps have no chordae or papillary muscles, so they do not depend on the papillary muscle that has failed.
DInterventricular septum loses its connection to the aorta
The interventricular septum is a muscular wall between the ventricles; it does not depend on papillary muscle function for its structure.
Reference: SCFHS Electrocardiograph Content Guideline (V1.220901), Cardiac Anatomy, p. 2; OpenStax, Anatomy and Physiology 2e, 19.1 Heart Anatomy
Ask a friend
02A patient with strong vagal stimulation has a slow sinus rate. Which change at the cellular level of the sinoatrial node best explains the slowing?
Practice question Unit: Cardiac Electro-physiology
AThe nodal cells lose their prepotential and settle at a fixed resting potential of −90 mV
Nodal cells keep their prepotential under vagal influence; they never settle at −90 mV, a value belonging to ventricular muscle.
BAcetylcholine opens sodium and calcium channels, speeding the prepotential and shortening repolarization
Opening sodium and calcium channels is the effect of norepinephrine, and it would speed the rate rather than slow it.
CAcetylcholine opens potassium channels, slowing spontaneous depolarization and lengthening the time to the next threshold ✓ Correct answer
Vagal acetylcholine opens potassium channels, slowing spontaneous depolarization and extending repolarization, which delays the next beat.
DNorepinephrine binds beta-1 receptors, which slows the rate at which the prepotential reaches threshold
Norepinephrine from sympathetic nerves binds beta-1 receptors and speeds the rate; it is not the vagal mechanism that slows it.
Reference: SCFHS Electrocardiograph Content Guideline (V1.220901), Cardiac Electro-physiology, p. 2; OpenStax, Anatomy and Physiology 2e, 19.4 Cardiac Physiology
Ask a friend
03A patient taking sotalol has a sinus rate of about 120 beats per minute, and the machine's Bazett QTc reads 452 ms. Which statement is most appropriate?
Practice question Unit: Pharmacotherapy
ABazett under-corrects at this rate, so the true QTc is longer
Bazett under-corrects below 60 bpm, not above 100 bpm; at 120 bpm it tends to over-correct, so the true value is likely lower.
BA QTc can only be used when the rate is exactly 60
The QTc estimates QT at 60 bpm for any rate; raw QT is used only when the rate happens to be 60.
CBazett over-corrects here, so use Fridericia ✓ Correct answer
Bazett over-corrects above 100 bpm, so the reading may be overestimated; Fridericia or Framingham are more accurate outside 60-100 bpm.
DBazett is accurate at every rate, so the value stands
Bazett is only adequate between 60 and 100 bpm; outside that range its error grows and other formulas are preferred.
Reference: SCFHS Electrocardiograph Content Guideline (V1.220901), Pharmacotherapy, p. 2
Ask a friend
04A man with chest pain has horizontal ST depression in leads III and aVF only. What is the best interpretation before the technician reports?
Practice question Unit: Ischemic Heart Disease
AIt shows inferior ischaemia limited to that wall and needs no further review
Subendocardial ischaemia does not localise to a wall, so calling this inferior ischaemia misses a possible high lateral STEMI.
BIt may be reciprocal change, so check the high lateral leads for ST elevation ✓ Correct answer
Depression confined to one territory more likely reflects reciprocal change from STEMI, so aVL and lead I should be inspected for subtle ST elevation.
CIt proves widespread subendocardial ischaemia needing repeat right-chest leads
Widespread subendocardial ischaemia would involve many leads such as I, II and V4-6; right-chest leads are for suspected right ventricular infarction.
DIt is a normal variant because it is confined to two leads
Horizontal ST depression with chest pain is not a normal variant, and its limited distribution is exactly what raises suspicion of reciprocal change.
Reference: SCFHS Electrocardiograph Content Guideline (V1.220901), Ischemic Heart Disease, p. 2
Ask a friend
05A patient with aortic stenosis has an S wave of 22 mm in V1, an R wave of 16 mm in V5 and an R wave of 12 mm in V6. Using the Sokolow-Lyon rule, what is the conclusion?
Practice question Unit: Valvular Heart Disease
AThe voltage criterion for LVH is met ✓ Correct answer
Sokolow-Lyon uses S in V1 plus the taller of the V5 or V6 R wave: 22 + 16 = 38 mm, which is at least 35 mm.
BThe rule cannot be applied without lead aVL
Lead aVL belongs to the Cornell rule; Sokolow-Lyon needs only V1 and V5 or V6.
CThe criterion is not met because S in V1 is under 35 mm
The S wave in V1 is never judged alone; it is added to the R wave, so being under 35 mm does not decide anything.
DThe criterion is met only when the V6 R wave is also added
Only the taller R wave of V5 or V6 is added, so adding V6 as well is not part of the rule.
Reference: SCFHS Electrocardiograph Content Guideline (V1.220901), Valvular Heart Disease, p. 2
Ask a friend
06This strip is from a pale, clammy patient who has just lost blood after surgery. What should the technician tell the nurse?
Practice question Unit: Tachy-arrhythmias
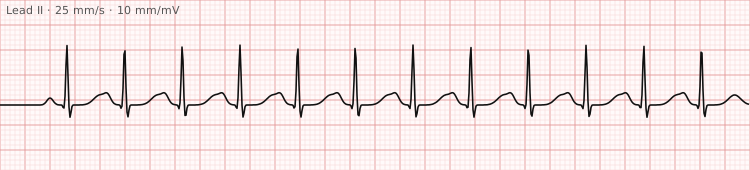
AThe rhythm is an atrial arrhythmia, so the patient needs an urgent anticoagulant dose
The P wave before each QRS shows sinus origin, not an atrial arrhythmia, and anticoagulation would not address blood loss.
BA primary rhythm disorder, so the patient needs urgent electrical cardioversion
Sinus tachycardia is normally secondary to another problem, so cardioversion is not the response; the underlying cause is sought and treated.
CA likely response to a cause such as blood loss, so the patient needs prompt review ✓ Correct answer
Sinus tachycardia is usually secondary, and hypovolaemia is a listed cause, so the technician reports the signs for the clinician to find the cause.
DThe rate is a normal finding after surgery, so the patient needs no clinical review now
A fast rate in a pale, clammy patient with blood loss is not safe to dismiss; hypovolaemia is a recognised cause that needs review.
Reference: SCFHS Electrocardiograph Content Guideline (V1.220901), Tachy-arrhythmias, p. 2
07A 58-year-old woman who recently began a new tablet for blood pressure reports dizziness. Her resting ECG is shown. Which explanation best fits the rhythm and history?
Practice question Unit: Brady-arrhythmias
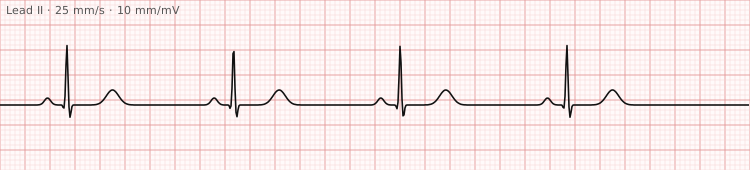
AFever from a chest infection speeding up the node
Fever and sepsis are listed causes of sinus tachycardia, which speeds the rate rather than producing a rate like this.
BA beta-blocker slowing the sinus node ✓ Correct answer
Beta-blockers are a recognised pharmacological cause of sinus bradycardia, matching the slow regular sinus rhythm and the new medicine.
CExcess thyroid hormone driving the node faster
Hyperthyroidism is listed as a cause of sinus tachycardia; a slow rate would point towards hypothyroidism instead.
DPain increasing her vagal tone and slowing the rate
Pain can slow the heart through vagal stimulation, but nothing suggests pain here, and a new drug is the better explanation.
Reference: SCFHS Electrocardiograph Content Guideline (V1.220901), Brady-arrhythmias, p. 2
08A narrow-complex tachycardia at about 150 beats per minute is recorded at standard settings, and the doctor cannot tell whether flutter waves are hidden between the QRS complexes. Which change to the recording would help most?
Practice question Unit: Technical aspect of 12 LEAD ECG
ARepeat the strip at half standard gain so the QRS complexes look smaller
Lower gain shrinks all waveforms, including small flutter waves, so atrial activity becomes harder to find.
BRepeat the strip at 50 mm/s so the waves are spread further apart ✓ Correct answer
A faster paper speed of 50 mm/s spreads out the trace so atrial waves in a 2:1 ratio to the QRS become clearer.
CRepeat the strip at 10 mm/s so that many more beats fit on one page
Slower paper squeezes everything closer together, making hidden atrial waves harder to see, not easier.
DRepeat the strip with all six chest electrodes moved to the right chest
A right-sided set is used for suspected right ventricular infarction and does not help to find atrial waves.
Reference: SCFHS Electrocardiograph Content Guideline (V1.220901), Technical aspect of 12 LEAD ECG, p. 2
Ask a friend
09A magnet is applied to a patient's implanted device. Which statement about the response is correct?
Practice question Unit: Pacemakers and Defibrillators
ABoth devices are deactivated for as long as the magnet stays in place
Only the defibrillator is deactivated; a pacemaker keeps delivering stimuli, typically at a fixed rate with no sensing.
BA pacemaker usually paces asynchronously; a defibrillator is deactivated ✓ Correct answer
Magnet mode on a pacemaker generally gives asynchronous pacing, while a magnet on an implantable cardioverter defibrillator deactivates shock delivery.
CBoth devices usually switch to asynchronous constant-rate pacing
Asynchronous pacing is the pacemaker response only; a defibrillator treated this way would simply have its therapy deactivated.
DA pacemaker is deactivated, whereas an implanted defibrillator paces asynchronously
This reverses the two responses; a magnet does not switch a pacemaker off and does not make a defibrillator pace asynchronously.
Reference: SCFHS Electrocardiograph Content Guideline (V1.220901), Pacemakers and Defibrillators, p. 2
Ask a friend
10A footballer collapses mid-match, is unresponsive, and jerks his limbs for a few seconds, then lies still. He appears to pant quickly. What is the best action?
Practice question Unit: Basic Life Support
ADelay CPR until the panting stops completely
Waiting for panting to stop wastes time; panting or gasping in an unresponsive person is an abnormal pattern that signals cardiac arrest, so CPR starts at once.
BCall for help and start CPR, because cardiac arrest is assumed ✓ Correct answer
Recognising arrest despite brief seizure-like jerks and abnormal panting, the rescuer calls for help and starts CPR without waiting.
CPlace him in the recovery position because he is still breathing
Panting is an abnormal pattern that athletes may show early in arrest; it does not count as normal breathing, so the recovery position is wrong.
DTreat it as a seizure and wait for him to wake up on his own
Brief seizure-like movement can occur at the onset of cardiac arrest; once it stops, breathing must be assessed rather than assuming a seizure.
Reference: SCFHS Electrocardiograph Content Guideline (V1.220901), Basic Life Support, p. 2; Resuscitation Council UK, Adult basic life support Guidelines (2025)
Ask a friend
